Version 1.0 — Published September 2026
Quick Answer
Perforated peptic ulcer is a classic acute-abdomen scenario on NEET PG. A 55-year-old chronic NSAID user with sudden severe epigastric pain, board-like abdomen, fever, tachycardia, WBC 18,000 and free air under both domes of the diaphragm on erect chest X-ray needs an 8-step approach:
- Recognise the pattern — sudden onset epigastric pain radiating to shoulder, boardlike abdomen, silent belly, NSAID or peptic-ulcer risk factor = perforated viscus until proven otherwise
- Resuscitate — two large-bore IV cannulae, isotonic crystalloid, NPO, NG decompression, Foley, blood cultures
- Broad-spectrum IV antibiotics — piperacillin-tazobactam or a carbapenem; add anaerobic and enterococcal cover
- IV proton pump inhibitor — pantoprazole 80 mg bolus then 8 mg per hour infusion
- Confirm with erect chest X-ray — pneumoperitoneum; CT abdomen with IV contrast if diagnosis unclear
- Urgent surgical consultation — laparotomy or laparoscopy for Graham omental patch on an anterior duodenal perforation
- Non-operative management is reserved for a select subset — stable, walled-off, non-septic, small pneumoperitoneum
- H. pylori eradication and NSAID cessation after recovery to prevent recurrence
The case
A 55-year-old retired schoolteacher is brought to a district hospital emergency department by his son with sudden severe epigastric pain 6 hours ago. The pain began abruptly while he was watching television and was so intense that he doubled over; it now radiates to the right shoulder, is constant, and worsens with any movement. He describes it as "the worst pain I have ever felt." He has vomited once (non-bilious) and feels nauseated but has not vomited again. He is unable to sit up straight and prefers to lie completely still.
Past medical history — bilateral knee osteoarthritis for the past 8 years for which he has been taking over-the-counter diclofenac 50 mg twice daily and occasionally ibuprofen for at least 6 years, without gastric protection. Long-standing dyspepsia treated intermittently with antacids purchased over the counter. Two episodes of upper abdominal pain in the past 2 years were attributed to gastritis by a local practitioner; endoscopy was never performed.
Other history — type 2 diabetes on metformin 500 mg twice daily, HbA1c last checked 7.4 percent. Hypertension on amlodipine 5 mg. Non-smoker. Occasional alcohol.
On examination — appears distressed and diaphoretic, lying supine and completely still, taking shallow breaths. Temperature 38.4 degrees Celsius. Pulse 115 per minute, regular. Blood pressure 100/60 mmHg. Respiratory rate 26 per minute. SpO2 96 percent on room air. Capillary refill 3 seconds. Cold peripheries.
Abdomen — reduced respiratory movement; board-like rigidity across the entire abdomen with involuntary guarding; generalised tenderness most marked in the epigastrium; severe rebound tenderness in all four quadrants; percussion painful; bowel sounds absent on 3 minutes of auscultation. No visible peristalsis. No stigmata of chronic liver disease. No inguinal hernias.
Digital rectal examination — non-tender, empty rectum, no mass, no blood on the glove.
Cardiovascular and respiratory — sinus tachycardia, no murmur; clear breath sounds bilaterally, mild bibasal hypoventilation from splinting.
CNS — alert and oriented, in obvious pain, no meningism, no focal deficit.
Working diagnosis: acute generalised peritonitis, likely perforated peptic ulcer.
Initial assessment and time-critical resuscitation
A — Airway: patent, speaking in short sentences.
B — Breathing: RR 26, SpO2 96 on RA, splinting from abdominal pain.
C — Circulation: compensated shock — HR 115, BP 100/60, cool peripheries, CRT 3 seconds, lactic-acidosis picture on ABG.
D — Disability: alert.
E — Exposure: febrile, no rash, no stigmata of chronic disease.
Two 16G cannulae inserted; isotonic crystalloid 1 litre over 30 minutes then reassess (avoid over-resuscitation in sepsis where aggressive Hartmann/Ringer boluses per the Surviving Sepsis 30 mL/kg guidance are titrated to physiological response). NPO kept. NG tube inserted on free drainage decompresses the stomach and reduces further peritoneal contamination. Foley catheter placed to monitor hourly urine output at 0.5-1 mL/kg per hour. Blood samples drawn for a full septic screen and cross-match. IV analgesia — morphine 5 mg titrated to comfort (does not mask peritoneal signs in the modern era). Empirical broad-spectrum antibiotics — piperacillin-tazobactam 4.5 g IV every 8 hours (or meropenem 1 g every 8 hours in units with high resistance) with anaerobic, enterococcal and gram-negative cover. IV proton pump inhibitor — pantoprazole 80 mg bolus then 8 mg per hour infusion. Urgent surgical consultation.
Tier 1 investigations (immediate)
- CBC — Hb 14 g/dL, WBC 18,000 per microlitre with left shift (81 percent neutrophils), platelets 210,000
- Renal panel — urea 45 mg/dL, creatinine 1.4 mg/dL (pre-renal AKI on chronic baseline), Na 138, K 4.2, HCO3 18
- Glucose — 155 mg/dL (stress hyperglycaemia on background T2DM)
- LFT — bilirubin 1.0, AST 34, ALT 28, albumin 3.5, alkaline phosphatase 96
- Amylase — 220 U/L (mildly elevated; can be seen in perforation because pancreatic enzymes leak transperitoneally)
- Lipase — 90 U/L (normal — argues against primary pancreatitis)
- CRP — 145 mg/L
- ABG — pH 7.32, pCO2 32, HCO3 18, lactate 3.8 mmol/L (compensated metabolic acidosis with rising lactate)
- Coagulation — normal
- Cross-match 2 units packed red cells
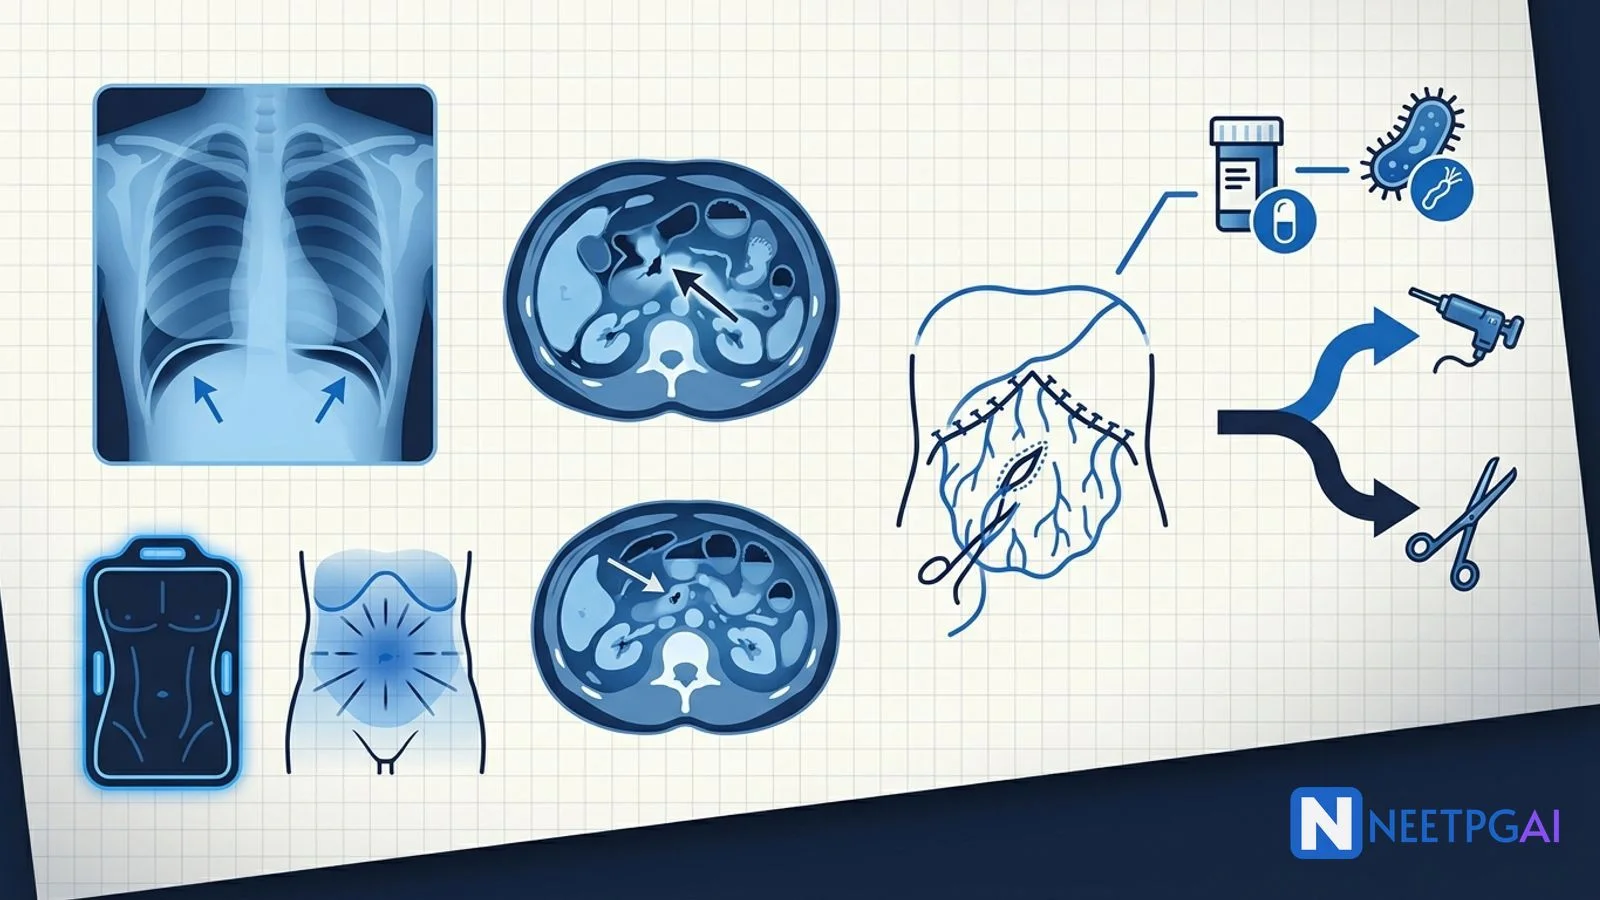
- Erect chest X-ray — free air under both hemidiaphragms (bilateral subdiaphragmatic pneumoperitoneum)
- CT abdomen with IV contrast (avoiding oral contrast in suspected perforation) — free air anterior to the liver and around the falciform ligament, free fluid in the pelvis and hepatorenal recess, focal wall thickening of the anterior duodenal bulb with adjacent inflammatory stranding, no free enteric contrast (sealed at the time of scan)
Interpretation: confirmed pneumoperitoneum with radiological features of anterior duodenal perforation; systemic inflammatory response with early sepsis physiology and pre-renal acute kidney injury.
Differential and classification
The Indian surgical differential for a sudden-onset acute abdomen with signs of peritonism:
- Perforated peptic ulcer (most likely given NSAID history and history)
- Acute pancreatitis — pain radiates to the back; lipase substantially raised (usually more than 3 times normal); imaging shows peripancreatic inflammation
- Mesenteric ischaemia — pain out of proportion to signs; atrial fibrillation, atherosclerosis; late lactic acidosis
- Ruptured abdominal aortic aneurysm — elderly, pulsatile mass, hypotension
- Acute cholecystitis or gallbladder perforation — right upper quadrant tenderness, Murphy sign
- Perforated appendicitis — migratory right lower quadrant pain, McBurney tenderness
- Perforated Meckel diverticulum, colonic diverticulitis or malignancy — usually left lower quadrant
- Ruptured ectopic pregnancy — reproductive-age woman with amenorrhoea, positive urine beta-hCG (not this patient)
- Testicular torsion, ovarian torsion, ureteric colic — different pain patterns
- Medical mimics — inferior wall MI with referred epigastric pain, DKA, adrenal crisis, sickle cell crisis, lower lobe pneumonia
Peritonitis classification
- Primary (spontaneous bacterial peritonitis) — monomicrobial, no anatomical breach, classically in cirrhotic ascites; managed medically with cefotaxime
- Secondary — anatomical breach or perforation of a hollow viscus; polymicrobial; requires source control (surgery or drainage) plus antibiotics
- Tertiary — persistent or recurrent peritonitis despite adequate treatment; often multidrug-resistant organisms and Candida
This patient has secondary peritonitis from a perforated peptic ulcer.
Perforated peptic ulcer — specifics
- Duodenal ulcer perforation is 4 times more common than gastric ulcer perforation
- Risk factors: NSAID use (this patient), H. pylori infection, smoking, alcohol, corticosteroids, physiological stress (ICU stress ulcers), Zollinger-Ellison syndrome
- Anatomy: the anterior wall of the first part of the duodenum is the commonest site of free perforation; posterior wall ulcers tend to erode into the pancreas (penetration) or the gastroduodenal artery (haemorrhage) rather than perforate freely
The diagnostic and management workflow
Immediate management
- Resuscitation — IV fluids titrated to physiological response, NPO, NG decompression, Foley
- Broad-spectrum antibiotics — piperacillin-tazobactam or carbapenem
- IV PPI — pantoprazole 80 mg bolus then 8 mg per hour infusion
- Analgesia — opioids titrated
- Surgical consultation and consent for laparotomy or laparoscopy
Definitive management — surgery
The surgical management gold standard is prompt operative repair.
- Primary closure with a Graham omental patch — a pedicled tongue of omentum drawn up and secured over the perforation with interrupted sero-serosal sutures, providing a vascular scaffold for healing. Standard for small (less than 10 mm) anterior duodenal perforations
- Modified Graham patch — primary suture closure of the defect followed by omental reinforcement
- Truncal vagotomy plus pyloroplasty or antrectomy plus vagotomy (Billroth I or II) — reserved for large perforations, giant ulcers, bleeding, suspected malignancy on frozen section, or patients who have failed medical therapy and had a repeat perforation
- Wedge excision and closure — for gastric ulcer perforation with mandatory biopsy of the ulcer edge to exclude malignancy
- Peritoneal lavage — copious warm saline lavage of all four quadrants; drain placement in high-risk closures
Approach choice — laparoscopic repair is safe and effective for stable patients in units with the expertise, with faster recovery and shorter hospital stay; open laparotomy is preferred in unstable patients, unclear diagnosis, or complex reconstructive requirements.
Non-operative (conservative) management
The Crofts (Taylor) regimen — IV fluids, NPO, NG decompression, IV antibiotics, IV PPI, close monitoring — is reserved for a highly select subgroup:
- Haemodynamically stable
- Non-septic
- Walled-off perforation on CT with a small collection
- Small (less than 10 mm) pneumoperitoneum
- High operative risk (severe comorbidity, extreme frailty) making surgery prohibitive
- Resource-limited settings without surgical access
Success rates are 40-70 percent in appropriately selected patients but strict serial monitoring with a low threshold to convert to surgery is essential. This patient is septic, has generalised peritonitis, and needs surgery.
H. pylori eradication
All patients treated for peptic ulcer perforation must be tested for H. pylori (intra-operative antral biopsy, urea breath test or stool antigen after recovery). Standard regimens:
- Triple therapy — PPI twice daily plus amoxicillin 1 g twice daily plus clarithromycin 500 mg twice daily for 14 days (where clarithromycin resistance is under 15 percent)
- Bismuth quadruple therapy — PPI twice daily plus bismuth subsalicylate plus metronidazole plus tetracycline for 10-14 days (where clarithromycin resistance is high or after failure)
- Concomitant therapy — PPI plus amoxicillin plus clarithromycin plus metronidazole for 10-14 days
Confirm eradication with urea breath test or stool antigen at 4-8 weeks after therapy, ideally after stopping PPI for 2 weeks.
NSAID counselling
- Stop NSAIDs where possible; switch to paracetamol for OA pain
- If NSAIDs are unavoidable, use the lowest effective dose for the shortest possible duration with a concomitant PPI and consider COX-2 selective agents (celecoxib) in patients at high GI risk balanced against cardiovascular risk
Diagnosis
Perforated anterior duodenal ulcer with generalised secondary bacterial peritonitis and early septic physiology, in a chronic NSAID user with untreated H. pylori background — for urgent resuscitation, broad-spectrum antibiotics, IV PPI and emergency laparotomy for Graham omental patch, with post-operative H. pylori testing and eradication plus NSAID cessation.
Complications and post-operative course
Acute post-operative
- Septic shock and multi-organ dysfunction — the leading cause of early post-operative death
- Surgical site infection — 10-15 percent after emergency laparotomy for perforation
- Intra-abdominal abscess — subphrenic, subhepatic, or pelvic collections managed with percutaneous drainage
- Enterocutaneous fistula at the repair site
- Anastomotic leak — if a formal resection has been done
- Prolonged ileus, aspiration pneumonia, DVT/PE, AKI
Late
- Gastric outlet obstruction from scarring of the pyloric channel
- Adhesive small bowel obstruction
- Recurrent ulceration if H. pylori is not eradicated or NSAIDs are resumed without gastroprotection
- Malnutrition and delayed return to full oral intake
Prognosis and Boey scoring
The Boey score uses three variables — pre-operative shock (systolic BP under 100 mmHg), major medical illness, and duration of perforation over 24 hours — to predict operative mortality:
| Boey score | Mortality |
|---|
| 0 | 0 percent |
| 1 | 10 percent |
| 2 | 45 percent |
| 3 | 100 percent |
Overall mortality ranges from 2-5 percent with early presentation to 25-40 percent with delayed presentation in septic shock.
India-specific considerations
- Delayed presentation is common — long distances to referral centres, initial primary-care treatment with antacids or self-medication, and lack of insurance
- NSAID over-the-counter culture — musculoskeletal pain, headache, backache and menstrual pain drive widespread self-purchase without pharmacist screening or gastroprotection
- H. pylori prevalence in India is high — 60-80 percent of adults in some series — reflecting crowded living, water contamination and childhood transmission
- PMJAY coverage for emergency laparotomy is broadly available at empanelled hospitals but implant, ICU and post-operative rehabilitation costs remain out-of-pocket in many rural settings
- Tertiary surgical access — a district hospital surgeon typically performs the Graham patch; formal resection, ICU care and management of complications may need referral
- Antibiotic stewardship — Indian units face high rates of ESBL-producing gram-negative and carbapenem-resistant organisms; empirical carbapenem use is guided by local antibiograms
How NEET PG tests perforated peptic ulcer
Recurring patterns:
Pattern 1 — Sudden severe epigastric pain radiating to shoulder + board-like abdomen + free air under diaphragm — perforated peptic ulcer.
Pattern 2 — Commonest site of duodenal perforation — anterior wall of the first part of the duodenum.
Pattern 3 — Posterior duodenal ulcer complication — penetration into the pancreas, or haemorrhage from the gastroduodenal artery.
Pattern 4 — Best imaging modality — erect chest X-ray for pneumoperitoneum (as little as 1-2 mL of free air); CT abdomen with IV contrast if unclear.
Pattern 5 — Definitive management — emergency laparotomy or laparoscopy with Graham omental patch for anterior duodenal perforation.
Pattern 6 — Boey score — three variables predicting operative mortality.
Pattern 7 — H. pylori — triple or quadruple therapy with confirmation of eradication at 4-8 weeks.
Pattern 8 — Amylase in perforation — mildly elevated (from transperitoneal absorption of pancreatic enzymes), typically under 3 times normal; lipase usually normal.
High-yield one-liners:
- Anterior duodenal ulcer perforates; posterior duodenal ulcer bleeds (gastroduodenal artery) or penetrates (pancreas)
- Erect chest X-ray identifies as little as 1-2 mL of free intraperitoneal air
- Left lateral decubitus film if the patient cannot stand
- Rigler sign — air on both sides of the bowel wall (supine film)
- Graham omental patch is the standard operation for a small anterior duodenal perforation
- Antrectomy plus vagotomy is reserved for giant ulcers, bleeding, or suspected malignancy
- Non-operative management is a highly selective option in stable, walled-off, non-septic patients
- H. pylori eradication reduces one-year recurrence from around 60 percent to under 5 percent
- Boey score predicts operative mortality
- Amylase in perforation is mildly raised; lipase is usually normal — pancreatitis is not
- Peritonitis classification — primary (SBP), secondary (perforation), tertiary (persistent)
Frequently Asked Questions
How does one differentiate peritonitis from other causes of acute abdomen at the bedside?
Peritonitis produces a characteristic constellation on inspection, palpation and percussion. The patient lies still (in contrast to renal colic where they roll about), with rapid shallow breathing to avoid diaphragmatic excursion; the abdomen does not move with respiration. Palpation reveals involuntary guarding progressing to a rigid board-like abdomen, generalised tenderness and rebound. Percussion is exquisitely painful; bowel sounds are absent in generalised peritonitis. The three main mimics of surgical peritonitis are medical peritonism (referred pain from lower-lobe pneumonia, myocardial infarction, DKA, sickle-cell crisis, adrenal crisis, familial Mediterranean fever), spontaneous bacterial peritonitis in cirrhosis (usually a diffuse ache, mild tenderness, less rigidity) and mesenteric ischaemia (severe pain out of proportion to physical signs, at least early). A rigid abdomen with fever and shock in a patient on NSAIDs, steroids or with a peptic ulcer history should be treated as perforation until proven otherwise.
Which imaging modality confirms hollow viscus perforation and what are its pitfalls?
Free intraperitoneal air (pneumoperitoneum) is the imaging hallmark. Erect chest X-ray showing crescents of free air under the domes of the diaphragm is the classic exam finding and detects as little as 1-2 mL of free air in an optimally positioned patient. If the patient cannot stand, a left lateral decubitus abdominal film shows free air between the liver and the abdominal wall. Supine abdominal films are insensitive but may show the Rigler double-wall sign (air on both sides of the bowel wall), the football sign, or the falciform ligament sign. Erect chest is missed or underestimated in up to 30 percent of perforations because of subclinical perforation, sealed perforation, retroperitoneal perforation or an inadequately positioned patient. CT abdomen with IV contrast is far more sensitive (over 95 percent) and identifies the site of perforation via focal wall thickening, adjacent inflammatory stranding, extraluminal enteric contrast or free fluid. Oral contrast is avoided when perforation is suspected because it leaks into the peritoneum. Point-of-care ultrasound can identify free air with a characteristic enhancement of the peritoneal stripe.
What is the Graham omental patch and when is antrectomy indicated instead?
The Graham omental patch, described in 1937, is the standard operation for a perforated duodenal ulcer. A pedicled tongue of omentum is drawn up and secured over the perforation with interrupted sero-serosal sutures — the omentum plugs the defect and provides a vascular scaffold for healing. It is well suited to small anterior duodenal perforations (typically less than 10 mm) in a haemodynamically stable patient without a stigma of chronicity. A modified Graham patch primarily closes the defect with interrupted seromuscular sutures then reinforces with omentum. Antrectomy plus vagotomy (Billroth I or II) or highly selective vagotomy is reserved for large perforations (more than 20 mm), bleeding perforations, giant ulcers, suspected malignancy on frozen section, or in patients who have failed previous medical therapy and repeat perforation. In the modern era of profoundly effective PPI plus H. pylori eradication, definitive acid-reducing surgery is rare — Graham patch plus post-operative eradication is the workhorse.
How is H. pylori eradicated after a perforated peptic ulcer and why does this reduce recurrence?
H. pylori infection is documented in 60-90 percent of duodenal ulcers and 40-70 percent of gastric ulcers, and eradication of the organism reduces one-year recurrence from around 60 percent (untreated) to under 5 percent (successfully eradicated). All patients treated for a peptic ulcer perforation must be tested for H. pylori — urea breath test, stool antigen or intra-operative biopsy — and treated if positive. Standard first-line regimens include (1) clarithromycin-based triple therapy: PPI twice daily plus amoxicillin 1 g twice daily plus clarithromycin 500 mg twice daily for 14 days, appropriate where local clarithromycin resistance is under 15 percent; (2) bismuth-based quadruple therapy: PPI twice daily plus bismuth subsalicylate plus metronidazole plus tetracycline for 10-14 days, preferred where clarithromycin resistance is high or after treatment failure; and (3) concomitant therapy: PPI plus amoxicillin plus clarithromycin plus metronidazole for 10-14 days. Confirmation of eradication with urea breath test or stool antigen at 4-8 weeks after therapy is essential, ideally after stopping PPI for 2 weeks to avoid false negatives.
What is the expected mortality and morbidity after a perforated peptic ulcer and what drives outcome?
Mortality after perforated peptic ulcer ranges from 2-5 percent when patients present within 12 hours of perforation and undergo prompt surgical repair, to 25-40 percent when presentation is delayed beyond 24 hours, in septic shock, in the elderly (over 75 years), in those with severe comorbidities and in patients with a large or malignant perforation. The Boey score (three variables — pre-operative shock, major medical illness, and duration of perforation greater than 24 hours) predicts operative mortality of 0, 10, 45 and 100 percent for 0, 1, 2 and 3 factors respectively. Common post-operative complications include surgical site infection, intra-abdominal abscess, enterocutaneous fistula, dehiscence, pneumonia, and multi-organ dysfunction. Late complications include gastric outlet obstruction from scarring, adhesive small bowel obstruction, and — if H. pylori is not eradicated or NSAIDs are resumed without gastroprotection — ulcer recurrence and re-perforation.
This content is for educational purposes for NEET PG exam preparation. It is not a substitute for professional medical advice, diagnosis, or treatment. Clinical information has been reviewed by qualified medical professionals.
Written by: NEETPGAI Editorial Team
Reviewed by: Pending SME Review
Last reviewed: September 2026