Version 1.0 - Published October 2026
Quick Answer
Diabetic retinopathy progresses from mild NPDR (microaneurysms only) through moderate (haemorrhages, cotton wool spots, hard exudates), severe (4-2-1 rule: haemorrhages in 4 quadrants OR venous beading in 2 OR IRMA in 1), very severe (any two of the three), to PDR (neovascularisation NVE/NVD, pre-retinal or vitreous haemorrhage, traction detachment). Centre-involving diabetic macular oedema (DME) is treated with intravitreal anti-VEGF (bevacizumab, ranibizumab, aflibercept, faricimab, brolucizumab). High-risk PDR is treated with panretinal photocoagulation (PRP). Screen type 1 at 5 years post-diagnosis, type 2 at diagnosis, pregnant diabetics preconception plus each trimester.
Why This Matters for NEET PG and INI-CET
Diabetic retinopathy is the most tested retinal pathology on NEET PG and INI-CET because it integrates Ophthalmology, Internal Medicine (type 1 and type 2 diabetes natural history), and Public Health (screening schedules). Expect 1-2 direct ophthalmology MCQs per NEET PG paper on staging, the 4-2-1 rule, screening schedules, or anti-VEGF agents, plus clinical vignettes integrated into Medicine case stems.
INI-CET and FMGE lean on retinal image identification - a fundus photograph with microaneurysms, dot-blot haemorrhages, cotton wool spots, hard exudates, venous beading, IRMA, or neovascularisation (NVE/NVD) must be rapidly staged. The ETDRS and ICDR classifications, the ETDRS screening protocol, and the anti-VEGF revolution of the past 15 years are all core examinable material.
Beyond the exam, this is a disease that will be in your clinical life every day. India has approximately 101 million people with diabetes (2024 ICMR-INDIAB estimate) and roughly a third will develop retinopathy; approximately 7-10 million have sight-threatening retinopathy requiring treatment. Any physician, endocrinologist, or GP must know when to refer for retinal examination and understand the screening schedule.
Pathophysiology
Chronic hyperglycaemia damages the retinal microvasculature through multiple interacting mechanisms:
- Polyol pathway activation - excess glucose shunted through aldose reductase to sorbitol, osmotic stress on retinal cells
- Advanced glycation end products (AGEs) - cross-linking of proteins, basement membrane thickening
- Protein kinase C (PKC) activation - diacylglycerol accumulation causes vasodilation, increased permeability, growth factor release
- Oxidative stress and inflammation - reactive oxygen species, inflammatory cytokines
- VEGF upregulation - hypoxic retina releases vascular endothelial growth factor; drives permeability (DME) and neovascularisation (PDR)
Pericyte loss is the earliest histological change, followed by endothelial dysfunction, basement membrane thickening, capillary occlusion, microaneurysm formation, and progressive non-perfusion.
ETDRS Staging (ICDR Simplified Scale)
| Stage | Findings |
|---|
| No apparent retinopathy | Normal fundus |
| Mild NPDR | Microaneurysms only |
| Moderate NPDR | Microaneurysms + dot/blot haemorrhages + cotton wool spots + hard exudates (more than mild, less than severe) |
| Severe NPDR | 4-2-1 rule (see below) |
| Very severe NPDR | Any two of the three 4-2-1 criteria |
| PDR | Neovascularisation (NVE / NVD), pre-retinal haemorrhage, vitreous haemorrhage, traction retinal detachment |
The 4-2-1 Rule (Severe NPDR)
Severe NPDR is defined by ANY ONE of three findings:
- 4 - Intraretinal haemorrhages (greater than or equal to 20 per quadrant) in all FOUR quadrants
- 2 - Definite venous beading in TWO or more quadrants
- 1 - Prominent IRMA (intraretinal microvascular abnormalities) in ONE or more quadrants
Progression risk from severe NPDR to high-risk PDR: 15% at 1 year, 60% at 5 years.
High-Risk PDR (DRS Criteria)
High-risk PDR requires immediate treatment. Defined by:
- NVD greater than one-third disc area, OR
- Any NVD + vitreous or pre-retinal haemorrhage, OR
- NVE greater than half disc area + vitreous or pre-retinal haemorrhage
Risk of severe vision loss (less than 5/200 at 4 months) within 2 years: 25-40% without treatment, cut by half with PRP.
Clinical Features by Stage
Mild to Moderate NPDR
- Often asymptomatic
- Visual acuity usually normal
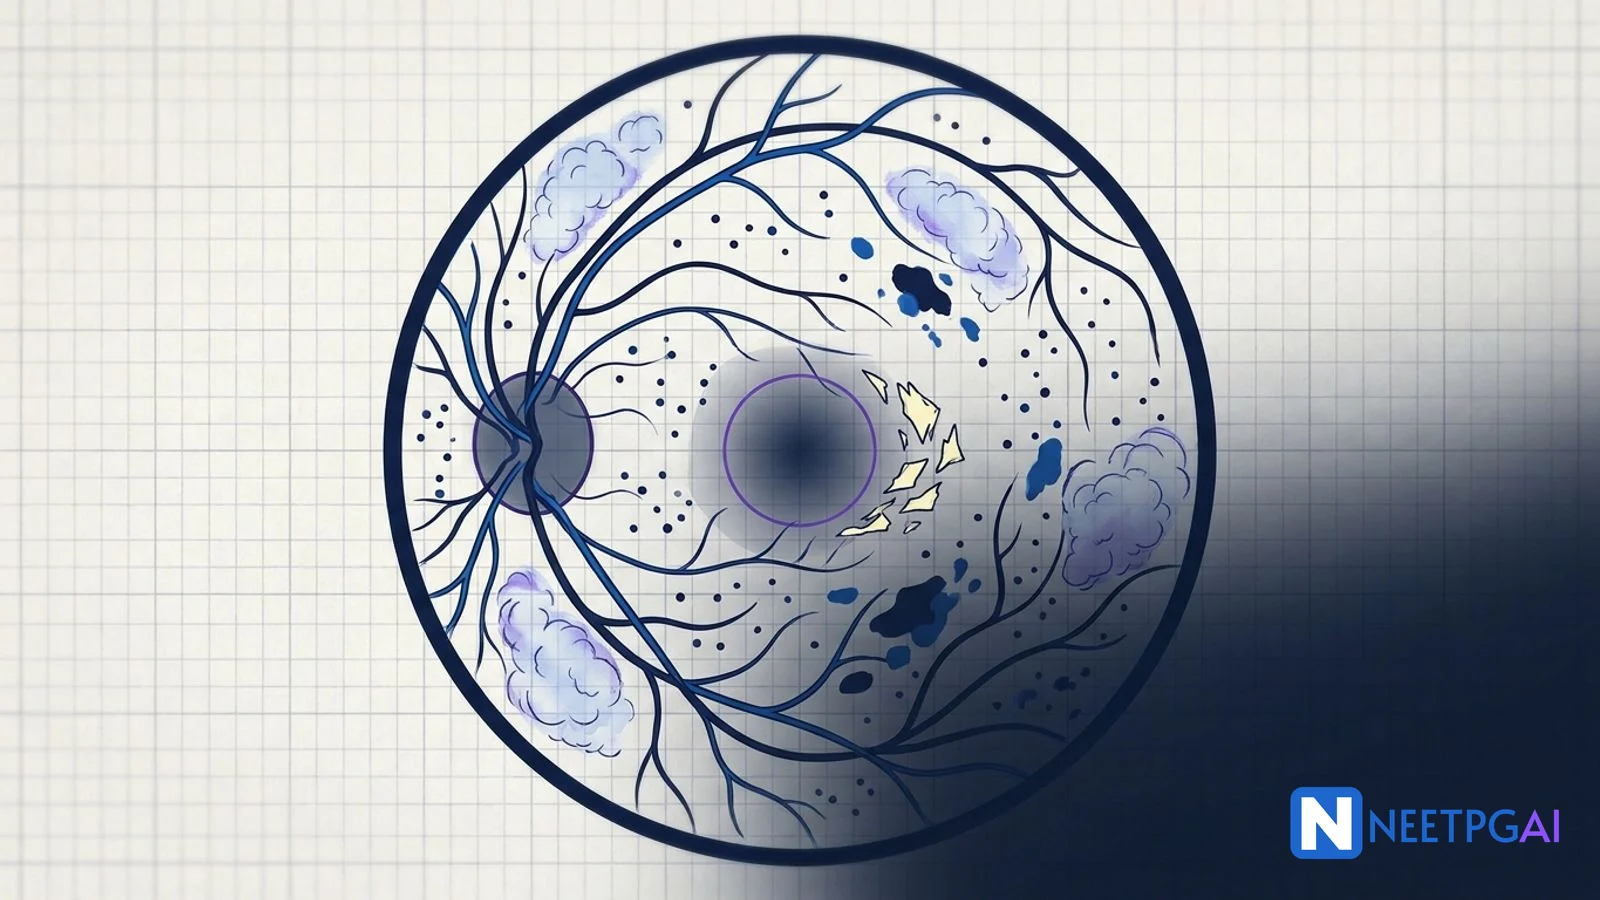
- Fundus: microaneurysms (tiny red dots adjacent to vessels), dot and blot haemorrhages (deep intraretinal), cotton wool spots (fluffy white nerve fibre layer infarcts), hard exudates (yellow-white lipid deposits at the junction of leaking vessels and normal retina)
Severe NPDR
- Still often asymptomatic
- Fundus: 4-2-1 features; venous beading looks like sausage-string vessel dilations; IRMA are abnormal shunt vessels between arterioles and venules within the retina (not neovascular - they do not break into vitreous)
- Fluorescein angiography shows capillary non-perfusion ("ischemic" areas)
PDR
- Floaters (vitreous haemorrhage)
- Sudden painless vision loss (vitreous haemorrhage or traction detachment)
- Fundus: new vessels at the disc (NVD) or elsewhere (NVE); fibrovascular proliferation; pre-retinal (sub-hyaloid) boat-shaped haemorrhage; vitreous haemorrhage obscuring the fundus
- Advanced: tractional retinal detachment, iris neovascularisation (NVI, rubeosis iridis), neovascular glaucoma
Diabetic Macular Oedema (DME)
ETDRS Clinically Significant Macular Oedema (CSME)
ANY of:
- Retinal thickening at or within 500 microns of the centre of the macula
- Hard exudates at or within 500 microns of the centre with adjacent retinal thickening
- Zone of thickening 1 disc area or larger, part of which is within 1 disc diameter of the centre
Treatment-Oriented Classification
| Type | Definition | Treatment |
|---|
| Non-centre-involving DME | Thickening within 1 disc diameter, central subfield spared | Observation OR focal/grid laser |
| Centre-involving DME | Central subfield thickness greater than or equal to 300 microns on SD-OCT with foveal thickening | Intravitreal anti-VEGF (first line) |
Vision loss correlates with centre-involving DME. OCT central subfield thickness is the key metric.
Investigations
Dilated Fundus Examination
Gold standard screening tool. Mydriasis with tropicamide 1% plus phenylephrine 2.5% (or tropicamide alone in dark irides); indirect ophthalmoscopy plus slit-lamp biomicroscopy with a 90 D or 78 D lens.
Optical Coherence Tomography (OCT)
Spectral-domain OCT is standard for DME diagnosis and monitoring.
- Central subfield thickness greater than or equal to 300 microns = centre-involving DME
- Detects subretinal fluid, intraretinal cysts, hard exudates, vitreomacular traction
- Monitors response to anti-VEGF therapy
Fundus Fluorescein Angiography (FFA)
Intravenous sodium fluorescein 5 mL of 10% solution; images taken 10-20 seconds (arterial), 30-60 seconds (early venous), 2-5 minutes (late).
- Microaneurysms: hyperfluorescent punctate dots in early phase
- Haemorrhages: hypofluorescent (block fluorescence)
- Capillary non-perfusion: dark patches = ischaemia
- NVE/NVD: profuse leakage in late phase
- DME: diffuse or focal leakage; cystoid macular oedema shows petaloid pattern
Ultra-Wide-Field Imaging
Optos ultra-wide-field colour and FFA capture up to 200 degrees of the retina in a single image - detects peripheral ischaemia and NVE missed on conventional 7-field photography.
B-Scan Ultrasonography
In vitreous haemorrhage obscuring the fundus - assesses for traction retinal detachment, intraocular tumour, posterior vitreous detachment.
Screening Schedule
| Patient group | First examination | Follow-up |
|---|
| Type 1 diabetes | 5 years after diagnosis | Annual |
| Type 2 diabetes | At diagnosis | Annual |
| Pregnancy with pre-existing diabetes | Preconception OR first trimester | Each trimester + 6 weeks postpartum |
| Gestational diabetes | NOT required | - |
| Mild NPDR | - | Annual |
| Moderate NPDR | - | 6-12 months |
| Severe NPDR | - | 2-4 months |
| High-risk PDR | - | 1-3 months after treatment |
| DME on anti-VEGF | - | Monthly during loading, then 1-4 months |
Sudden decrease in vision OR new floaters = urgent same-day assessment to exclude vitreous haemorrhage or retinal detachment.
Treatment Ladder
Systemic Control
Tight glycaemic control is the single highest-yield intervention and the only one that modifies natural history.
| Parameter | Target | Evidence |
|---|
| HbA1c | 6.5-7% | DCCT (type 1), UKPDS (type 2) |
| Blood pressure | Less than 140/90 (or less than 130/80 if albuminuria) | UKPDS, ACCORD-BP |
| LDL cholesterol | Less than 100 mg/dL | ACCORD-Lipid |
Fenofibrate reduced progression of DR by approximately 40% in the ACCORD-Lipid and FIELD studies, independent of lipid changes - an exam-tested result.
Anti-VEGF Agents
| Agent | Mechanism | Dose (intravitreal) | Approx. cost per dose (India) |
|---|
| Bevacizumab (Avastin) | Full-length anti-VEGF-A antibody (off-label) | 1.25 mg / 0.05 mL | Rs 1,000-3,000 |
| Ranibizumab (Lucentis) | Fab fragment anti-VEGF-A | 0.3 mg / 0.05 mL | Rs 25,000-30,000 |
| Aflibercept (Eylea) | VEGF trap (VEGF-A, B, PlGF) | 2 mg / 0.05 mL | Rs 35,000-45,000 |
| Faricimab (Vabysmo) | Bispecific anti-VEGF-A + Ang-2 | 6 mg / 0.05 mL | Rs 60,000 |
| Brolucizumab (Beovu) | Humanised single-chain anti-VEGF-A | 6 mg / 0.05 mL | Rs 50,000 |
Prices approximate reference from mid-2026 India.
Typical regimen (DME) - 5-6 monthly loading doses followed by treat-and-extend or PRN based on OCT and visual acuity.
Brolucizumab warning - intraocular inflammation and retinal vasculitis risk; patients counselled before use.
Laser Photocoagulation
| Laser | Indication | Technique |
|---|
| Focal | Non-centre-involving DME, treating microaneurysms | 50-100 micron spot, direct burn on microaneurysm |
| Grid | Diffuse non-centre-involving DME | 100-200 micron spots in grid pattern over oedema |
| Panretinal (PRP) | High-risk PDR, severe NPDR with risk factors, iris neovascularisation | 500-micron burns, 1,200-2,000 total, 2-3 sessions, mid-periphery and periphery sparing macula and arcades |
PRP mechanism: destruction of hypoxic peripheral retina reduces VEGF drive, causing regression of neovascularisation.
Intravitreal Steroids
Second-line for anti-VEGF non-responders or pseudophakic DME.
- Triamcinolone acetonide 4 mg / 0.1 mL (off-label, cheap, 3-month duration)
- Dexamethasone implant (Ozurdex) 0.7 mg (6-month biodegradable implant)
- Fluocinolone acetonide implant (Iluvien) 0.19 mg (3-year non-biodegradable)
Side effects: cataract (nearly universal), IOP rise (approximately 30% at 1 year), endophthalmitis, implant dislocation.
Vitrectomy
Pars plana vitrectomy indicated for:
- Non-clearing vitreous haemorrhage greater than 1-3 months
- Traction retinal detachment involving or threatening the macula
- Combined traction-rhegmatogenous retinal detachment
- Dense pre-macular sub-hyaloid haemorrhage
- Progressive fibrovascular proliferation despite PRP
Diabetic Retinopathy Vitrectomy Study (DRVS) showed benefit of early vitrectomy for severe type 1 PDR.
High-Yield One-Liners
- 4-2-1 rule defines severe NPDR: 20+ haemorrhages in 4 quadrants OR venous beading in 2 OR IRMA in 1.
- Very severe NPDR = any TWO of the three 4-2-1 criteria.
- High-risk PDR = NVD greater than one-third disc area OR any NVD + VH OR NVE greater than half disc area + VH.
- Centre-involving DME = central subfield thickness greater than or equal to 300 microns on OCT.
- CSME is the ETDRS definition; centre-involving DME is the modern treatment-oriented term.
- Screen type 1 DM at 5 years post-diagnosis; type 2 DM at diagnosis.
- Pregnant pre-existing diabetics: preconception + each trimester + 6 weeks postpartum.
- Gestational diabetes does NOT require retinopathy screening.
- Fenofibrate reduces DR progression (ACCORD-Lipid, FIELD) independent of lipid change.
- Bevacizumab (Avastin) is off-label but widely used in India for affordability.
- Aflibercept binds VEGF-A, VEGF-B, placental growth factor.
- Faricimab targets VEGF-A AND angiopoietin-2 - up to 16-week dosing intervals.
- Brolucizumab carries intraocular inflammation and retinal vasculitis risk.
- Anti-VEGF loading phase for DME: 5-6 monthly injections.
- PRP uses 500-micron burns, 1,200-2,000 total in 2-3 sessions.
- PRP spares the macula and major vascular arcades.
- PRP side effects: peripheral visual field loss, nyctalopia, cataract acceleration, DME worsening.
- Ozurdex is dexamethasone 0.7 mg biodegradable 6-month implant.
- Iluvien is fluocinolone 0.19 mg non-biodegradable 3-year implant.
- Vitrectomy for non-clearing vitreous haemorrhage greater than 1-3 months or traction detachment threatening macula.
- NVI (iris rubeosis) can cause neovascular glaucoma - urgent PRP plus anti-VEGF.
Common Mistakes
-
Mixing up 4-2-1 for severe NPDR vs the ICDR mild classification - the 4-2-1 rule is for severe NPDR, not any earlier stage. Mild NPDR has only microaneurysms.
-
Screening gestational diabetes for retinopathy - gestational diabetes does NOT require retinopathy screening because the duration of hyperglycaemia is too short. Pre-existing type 1 or type 2 diabetes in pregnancy does require intensified screening.
-
Treating centre-involving DME with laser first - focal/grid laser is for NON-centre-involving DME. Centre-involving DME demands anti-VEGF first-line.
-
Starting PRP before treating DME - PRP can transiently worsen macular oedema due to inflammatory response. If DME is present, treat with anti-VEGF first (or simultaneously) and complete PRP in staged sessions.
-
Mistaking NVE for IRMA - NVE lie on or anterior to the retinal surface and leak profusely on FFA (break through internal limiting membrane). IRMA are intraretinal shunt vessels that do not leak as much and do not break into the vitreous. IRMA is NPDR; NVE is PDR.
Related Topics on NEETPGAI
Practice This on NEETPGAI
Drill the ETDRS stages, 4-2-1 rule, DME classification, anti-VEGF agents, and PRP indications on real NEET PG and INI-CET PYQs. Our 28,000+ MCQ bank includes fundus-image-based IBQs with annotated microaneurysms, cotton wool spots, NVE, and NVD.
Start free on NEETPGAI - 28,000+ MCQs, real PYQs, mock tests simulating NEET PG 2026 pattern, and an AI tutor that will walk you through any fundus photograph or DR management vignette step by step.