Version 1.0 - Published October 2026
Quick Answer
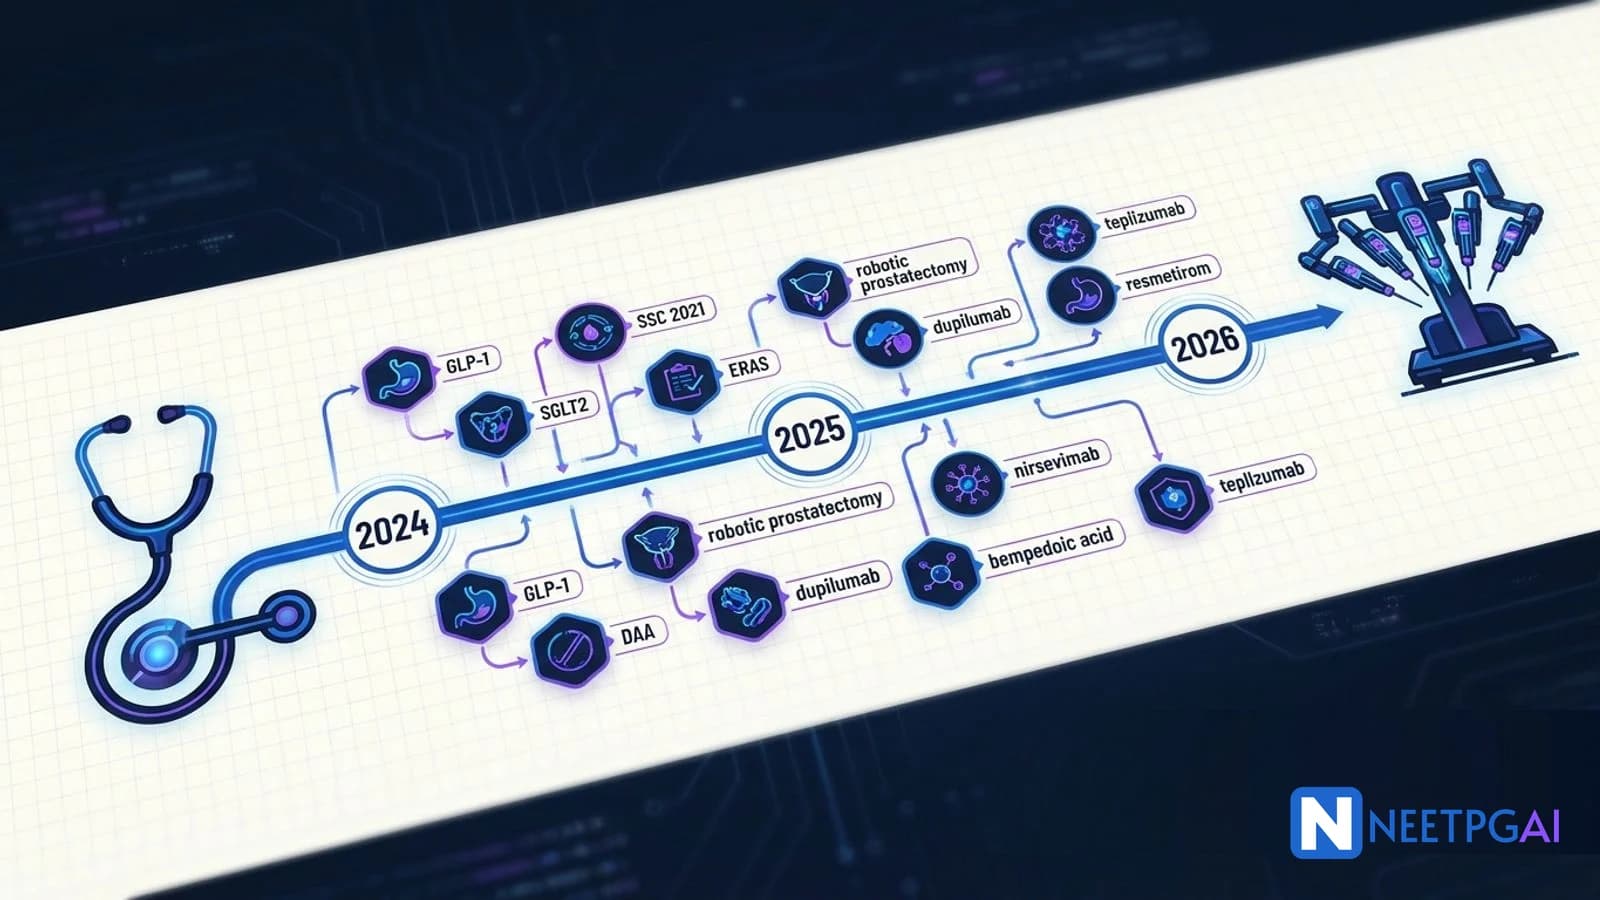
Recent advances carry 8-12 questions on INI-CET and 15-20 on NEET PG 2026, concentrated in GLP-1 and tirzepatide for obesity, SGLT2 for HFrEF-HFpEF-CKD, DAA-driven HCV elimination, Surviving Sepsis 2021 bundles, bempedoic acid, dupilumab, osimertinib for EGFR-NSCLC, immunotherapy, robotic prostatectomy, ERAS protocols, laparoscopic hernia repair, and bariatric surgery (LSG vs RYGB). Year-stamped evidence below.
Why This Matters for NEET PG & INI-CET
Recent advances are the single most examinable category in postgraduate medical entrance exams because the examiner needs new content every year to keep the paper discriminative. The AIIMS internal examiners and the NBEMS question bank both lean on the WHO essential medicines list updates, Indian national programme guideline updates, and the preceding 18-24 months of landmark trial publications. Every entry in this article is either on the current WHO essential medicines list, on an updated Indian national programme guideline (MoHFW, ICMR, NTEP), or anchored to a published landmark trial in 2024-2026.
Across INI-CET Nov 2023 to May 2025, recent advances contributed 8-12 marks per paper. On NEET PG 2026, the predicted contribution is 15-20 marks. The predictability of this zone is uniquely high - roughly 70% of recent-advances questions can be anticipated 6 months in advance from the trial literature. For aspirants targeting top-100 rank, this is the lowest-risk high-return cell on the exam-prep calendar.
Medicine - Endocrinology and Diabetes
GLP-1 agonists and dual GIP-GLP-1 agonists for obesity
Semaglutide (Wegovy 2.4 mg weekly SC, Ozempic 1-2 mg weekly SC for T2DM, Rybelsus 7-14 mg daily oral for T2DM) is now the dominant obesity drug. The STEP trial series (2021-2023) showed 15-17% weight loss at 68 weeks. The SELECT trial (2023) showed 20% cardiovascular event reduction in overweight and obese adults with established ASCVD but no diabetes.
Tirzepatide (Zepbound for obesity, Mounjaro for T2DM) is a dual GIP plus GLP-1 agonist. The SURMOUNT trial series showed 21-23% weight loss at 72 weeks - the largest pharmacological weight loss ever achieved. SURPASS trials showed superior HbA1c reduction versus semaglutide in T2DM.
Both drugs cause nausea and vomiting early in titration, pancreatitis rarely, and are contraindicated in medullary thyroid carcinoma and MEN2.
SGLT2 inhibitors - four indications now
Dapagliflozin and empagliflozin have four approved indications - T2DM (any HbA1c), HFrEF (DAPA-HF, EMPEROR-Reduced), HFpEF (EMPEROR-Preserved, DELIVER), and CKD with eGFR as low as 20 mL/min (DAPA-CKD, EMPA-KIDNEY). The HFrEF regimen is now four-pillar - ARNI, beta-blocker, MRA, SGLT2 - and should be started in all HFrEF patients unless contraindicated.
Classic adverse effects are euglycaemic DKA (glucose normal but severe acidosis - a classic exam trap), UTI, mycotic genital infections, Fournier gangrene (rare but severe), and volume depletion with hypotension early in therapy.
Teplizumab for T1DM
Teplizumab (anti-CD3 monoclonal, 14-day IV course) was approved by the FDA in 2022 for stage 2 T1DM (asymptomatic autoantibody-positive with dysglycaemia). It delays progression to clinical T1DM by at least 2 years. This is the first disease-modifying therapy for T1DM.
Resmetirom for MASH
Resmetirom (Rezdiffra, approved March 2024) is the first FDA-approved drug for metabolic dysfunction-associated steatohepatitis (MASH, formerly non-alcoholic steatohepatitis). It is a liver-selective thyroid hormone receptor beta agonist that reduces hepatic steatosis and fibrosis. The MAESTRO-NASH trial showed MASH resolution without fibrosis worsening in 25-30% of patients at 52 weeks.
Medicine - Hepatology and Infectious Disease
Direct-acting antivirals (DAAs) for HCV elimination
The current HCV treatment paradigm is universal eligibility, pan-genotypic 8-12 week oral regimen, cure rate greater than 95%. The two dominant regimens are:
- Sofosbuvir plus velpatasvir (Epclusa) - 12 weeks for most, 24 weeks with ribavirin for decompensated cirrhosis
- Glecaprevir plus pibrentasvir (Mavyret) - 8 weeks for treatment-naive without cirrhosis, 12 weeks with compensated cirrhosis
India's National Viral Hepatitis Control Program (NVHCP) provides free DAA treatment at government-approved centres. The WHO target is HCV elimination by 2030 - 90% diagnosis, 80% treatment, 65% mortality reduction.
Surviving Sepsis Campaign 2021 bundles
The hour-1 bundle elements:
| Element | Target |
|---|
| Measure lactate | Remeasure if initial >2 mmol/L |
| Obtain blood cultures | Before antibiotics but do not delay |
| Administer broad-spectrum antibiotics | Within 1 h for septic shock, within 3 h for sepsis without shock |
| IV fluid - 30 mL/kg crystalloid | Within 3 h for hypotension or lactate 4+ |
| Vasopressor | Maintain MAP 65+ mmHg; norepinephrine first-line |
Changes from the 2016 bundle - antibiotic timing is now stricter for shock (1 h) and relaxed for sepsis without shock (3 h), qSOFA is no longer recommended as a screening tool, and early goal-directed therapy with central venous oxygen monitoring is no longer required.
Medicine - Respiratory and Allergy
Dupilumab for type-2 inflammatory diseases
Dupilumab (anti-IL-4 receptor alpha, blocks both IL-4 and IL-13) is approved for five type-2 inflammatory diseases - severe atopic dermatitis (adult and pediatric), moderate-to-severe asthma with type-2 phenotype (blood eosinophils 150+ or FeNO 25+ ppb), chronic rhinosinusitis with nasal polyps, eosinophilic oesophagitis, and prurigo nodularis. The LIBERTY trials showed significant symptom reduction and oral steroid sparing in asthma. Conjunctivitis is the most common adverse effect.
GOLD 2024 COPD update
The 2024 GOLD guideline refined COPD groups into A, B, and E (eliminated the previous C and D). Group E now includes anyone with 2+ moderate exacerbations in the preceding year or 1+ exacerbation requiring hospitalisation. Group E patients should receive LABA plus LAMA plus ICS (triple therapy) from the start. Previous Group D (high symptom, high risk) was absorbed into Group E.
Medicine - Cardiology
Four-pillar HFrEF therapy
| Pillar | Drug | Mortality Benefit |
|---|
| RAS blockade | ARNI (sacubitril-valsartan) preferred over ACE/ARB | 20% |
| Beta-blocker | Metoprolol succinate, carvedilol, bisoprolol | 30% |
| MRA | Spironolactone, eplerenone, finerenone | 30% |
| SGLT2 inhibitor | Dapagliflozin, empagliflozin | 25% |
Start all four in the first 4-6 weeks after diagnosis. Vericiguat and ivabradine are second-line add-ons.
Bempedoic acid for LDL lowering
Bempedoic acid (approved 2020, CLEAR Outcomes trial 2023) is for statin-intolerant primary hypercholesterolaemia and ASCVD risk reduction. ATP-citrate lyase inhibition is two steps upstream of HMG-CoA reductase. It is a prodrug activated only in the liver, so skeletal muscle myalgia is absent. CLEAR Outcomes showed 13% MACE reduction over 3.4 years in statin-intolerant patients. Classical adverse effect is hyperuricaemia with gout flares.
LDL targets for 2026
| Risk Category | LDL Target |
|---|
| Very-high-risk ASCVD | <55 mg/dL |
| High-risk | <70 mg/dL |
| Moderate-risk | <100 mg/dL |
PCSK9 inhibitors (evolocumab, alirocumab) and inclisiran (siRNA, twice-yearly SC) are now routinely added when statin plus ezetimibe is insufficient to reach target.
Medicine - Oncology
Osimertinib for EGFR-mutated NSCLC
Osimertinib (Tagrisso) is a third-generation EGFR tyrosine kinase inhibitor active against the T790M resistance mutation. FLAURA (2017) established it as first-line for EGFR-mutated advanced NSCLC with superior PFS and CNS penetration. ADAURA (2020) extended its use to adjuvant therapy post-resection in stage IB-IIIA EGFR-mutated NSCLC, with 80% reduction in disease recurrence.
Immune checkpoint inhibitor landscape
| Drug | Target | Lead Indications |
|---|
| Pembrolizumab | PD-1 | NSCLC (PD-L1 50+), melanoma, Hodgkin, Merkel, MSI-high solid tumours |
| Nivolumab | PD-1 | Melanoma, NSCLC, RCC, Hodgkin, head and neck |
| Atezolizumab | PD-L1 | Urothelial, NSCLC |
| Durvalumab | PD-L1 | Stage III NSCLC consolidation after chemoradiation |
| Ipilimumab | CTLA-4 | Melanoma (combined with nivolumab) |
Immune-related adverse effects (irAE) include colitis, pneumonitis, thyroiditis, hepatitis, and hypophysitis - treat with high-dose corticosteroids, add infliximab if steroid-refractory.
Trastuzumab-deruxtecan for HER2-positive and HER2-low breast cancer
Trastuzumab-deruxtecan (Enhertu) is an antibody-drug conjugate (anti-HER2 trastuzumab linked to topoisomerase I inhibitor deruxtecan). DESTINY-Breast03 (2022) established it as second-line for HER2-positive metastatic breast cancer. DESTINY-Breast04 (2022) extended its use to HER2-low (IHC 1+ or 2+ FISH-negative) metastatic breast cancer - a previously untargetable category. The classical adverse effect is interstitial lung disease, which is fatal in a small percentage of patients and requires early recognition.
Surgery - Minimally Invasive and Robotic
Robotic prostatectomy
The da Vinci robotic platform is now standard in high-volume centres for localised prostate cancer. Compared to open radical prostatectomy, robotic prostatectomy offers equivalent oncologic outcomes (positive margins, biochemical recurrence), lower blood loss (300 vs 900 mL average), shorter catheter time (7 vs 14 days), and faster return to continence and potency. Open radical prostatectomy remains valid in low-volume centres and specific anatomical scenarios.
Robotic colorectal surgery
Robotic surgery particularly benefits low rectal cancer where the narrow pelvis makes laparoscopic TME challenging. The ROLARR trial (2017) showed no difference in conversion rates between robotic and laparoscopic right colectomy, but robotic approach reduced open conversion in low rectal cancer.
VATS and robotic thoracic lobectomy
Video-assisted thoracoscopic surgery (VATS) lobectomy for early-stage NSCLC has equivalent 5-year survival to open thoracotomy with lower complication rates and shorter length of stay. Robotic lobectomy is a newer option with similar outcomes to VATS.
Surgery - ERAS Protocols
The core ERAS elements for colorectal and other major surgery:
| Phase | Element |
|---|
| Preoperative | Carb loading up to 2 h before, no mechanical bowel prep (except left-sided colon with anastomosis), prehabilitation |
| Intraoperative | Minimally invasive approach, goal-directed fluid, normothermia, multimodal analgesia (TAP, epidural plus NSAID) |
| Postoperative | Early feeding (within 24 h), early mobilisation (day 0), early urinary catheter removal (24-48 h), no routine NG tube, DVT prophylaxis, opioid-sparing analgesia |
ERAS reduces length of stay by 2-3 days and complications by 30-50% across colorectal, hepatobiliary, bariatric, gynaecologic, urological, and thoracic surgery.
Surgery - Hernia and Bariatric
Laparoscopic inguinal hernia - TAPP vs TEP
| Feature | TAPP (Transabdominal Preperitoneal) | TEP (Totally Extraperitoneal) |
|---|
| Approach | Enter peritoneum, dissect preperitoneal space | Avoid peritoneum entirely |
| Learning curve | Shorter | Longer |
| Visualisation | Better in large hernias | More limited |
| Preferred for | Recurrent hernia, bilateral hernia, large hernia | Primary unilateral hernia |
| Complications | Bowel injury risk (enters peritoneum) | Peritoneal tear, pneumomediastinum |
Both have equivalent recurrence rates to open Lichtenstein tension-free mesh repair, with faster return to activity. The choice between TAPP and TEP is largely surgeon preference and anatomy.
Bariatric surgery - sleeve gastrectomy vs Roux-en-Y gastric bypass
| Feature | LSG (Laparoscopic Sleeve Gastrectomy) | RYGB (Roux-en-Y Gastric Bypass) |
|---|
| Mechanism | Restrictive (removes 75-85% stomach) | Restrictive plus malabsorptive |
| Excess weight loss (5 y) | 60-70% | 70-80% |
| T2DM remission | 60-75% | 80-85% |
| GORD outcome | May worsen (de novo GORD or worsening) | Improves GORD |
| Complications | Leak at long staple line, de novo GORD | Internal hernia, dumping syndrome, marginal ulcer, micronutrient deficiencies (B12, iron, calcium, folate) |
| Preferred for | Lower BMI, less metabolic disease, GORD-free | Severe T2DM, severe metabolic syndrome, GORD |
LSG is the single most common bariatric procedure globally. RYGB remains the gold standard for severe metabolic disease.
Pediatrics - Vaccines and Prevention
Nirsevimab for RSV
Nirsevimab (Beyfortus) is a long-acting anti-RSV F protein monoclonal antibody with a single-dose season-long effect. It is approved for all infants under 8 months entering their first RSV season and for high-risk children aged 8-19 months entering their second RSV season. In India, the drug is being rolled out through private channels in 2024-2026; UIP inclusion is under consideration.
HPV vaccination added to UIP (2024)
The Indian Universal Immunization Programme (UIP) added HPV vaccination for 9-14 year old girls in 2024. The vaccine (Cervavac - India-made quadrivalent, or imported Gardasil-9) prevents cervical, vaginal, vulval, anal, oropharyngeal cancers.
OBG - Updates
FIGO 2024 cervical cancer staging updates
The FIGO 2018 staging (which replaced FIGO 2009) remains the current standard. Key points - stage IB1 is now <2 cm, stage IB2 is 2-4 cm, stage IB3 is >4 cm; lymph node involvement makes stage IIIC regardless of local tumour size (IIIC1 pelvic, IIIC2 para-aortic).
Hypertensive disorders of pregnancy
Low-dose aspirin (75-150 mg daily starting at 12-16 weeks until 36 weeks) is now standard prophylaxis in women at high risk for pre-eclampsia (prior pre-eclampsia, chronic HTN, chronic kidney disease, diabetes, autoimmune disease, multiple risk factors). ACOG, NICE, and FIGO all endorse this.
High-Yield One-Liners
- Semaglutide 2.4 mg weekly SC achieves 15% weight loss; tirzepatide 15 mg weekly SC achieves 21%
- SELECT trial - semaglutide reduces cardiovascular events by 20% in overweight patients with ASCVD without diabetes
- SGLT2 inhibitors - approved for T2DM, HFrEF, HFpEF, and CKD (four indications)
- Four-pillar HFrEF - ARNI, beta-blocker, MRA, SGLT2 - start all four within 4-6 weeks
- Bempedoic acid activated only in liver - no muscle myalgia, raises uric acid
- LDL target in very-high-risk ASCVD is <55 mg/dL
- Teplizumab delays T1DM onset in stage 2 by at least 2 years (14-day anti-CD3 course)
- Resmetirom is the first FDA-approved drug for MASH (NASH) - 2024 approval
- DAA regimens for HCV - 8-12 weeks, pan-genotypic, cure rate >95%
- SSC 2021 - norepinephrine first-line vasopressor, MAP target 65 mmHg
- SSC 2021 - antibiotic within 1 h for septic shock, within 3 h for sepsis without shock
- Dupilumab blocks IL-4 receptor alpha - works on both IL-4 and IL-13
- Osimertinib - first-line for EGFR-mutated NSCLC (FLAURA) and adjuvant (ADAURA)
- Robotic prostatectomy - lower blood loss and shorter catheter time than open
- ERAS - carb loading up to 2 h pre-op, no mechanical bowel prep, early feeding
- LSG is restrictive only; RYGB is restrictive plus malabsorptive
- Nirsevimab - single-dose seasonal RSV prophylaxis for neonates and infants
- HPV added to UIP in 2024 for 9-14 year old girls
Common Mistakes
- Calling SGLT2 inhibitors diabetes-only. They treat HFrEF, HFpEF, and CKD independently of diabetes status.
- Giving dopamine as first-line vasopressor in septic shock. Norepinephrine is first-line in SSC 2021.
- Thinking qSOFA is still the SSC-recommended screening tool. SSC 2021 recommends against qSOFA screening alone; use NEWS or MEWS.
- Pairing LSG with severe T2DM. RYGB is preferred for severe metabolic disease - 80-85% diabetes remission versus 60-75% for LSG.
- Treating HER2-low breast cancer as untargetable. Trastuzumab-deruxtecan now has HER2-low indication after DESTINY-Breast04.
Related Topics on NEETPGAI
Practice This on NEETPGAI
NEETPGAI's open question bank includes 1,800+ recent-advances MCQs with year-stamped trial references and SME-reviewed explanations. All free for every registered aspirant - 28,000+ MCQs total, real community-reconstructed PYQs, section-locked INI-CET and NEET PG mock tests, and spaced-repetition revision. Pro features (AI Tutor, AI MCQ Generator, Clinical Case Simulator, AI Study Planner) layer on top. Sign up free and run your first recent-advances mock in 60 seconds.