Quick Answer
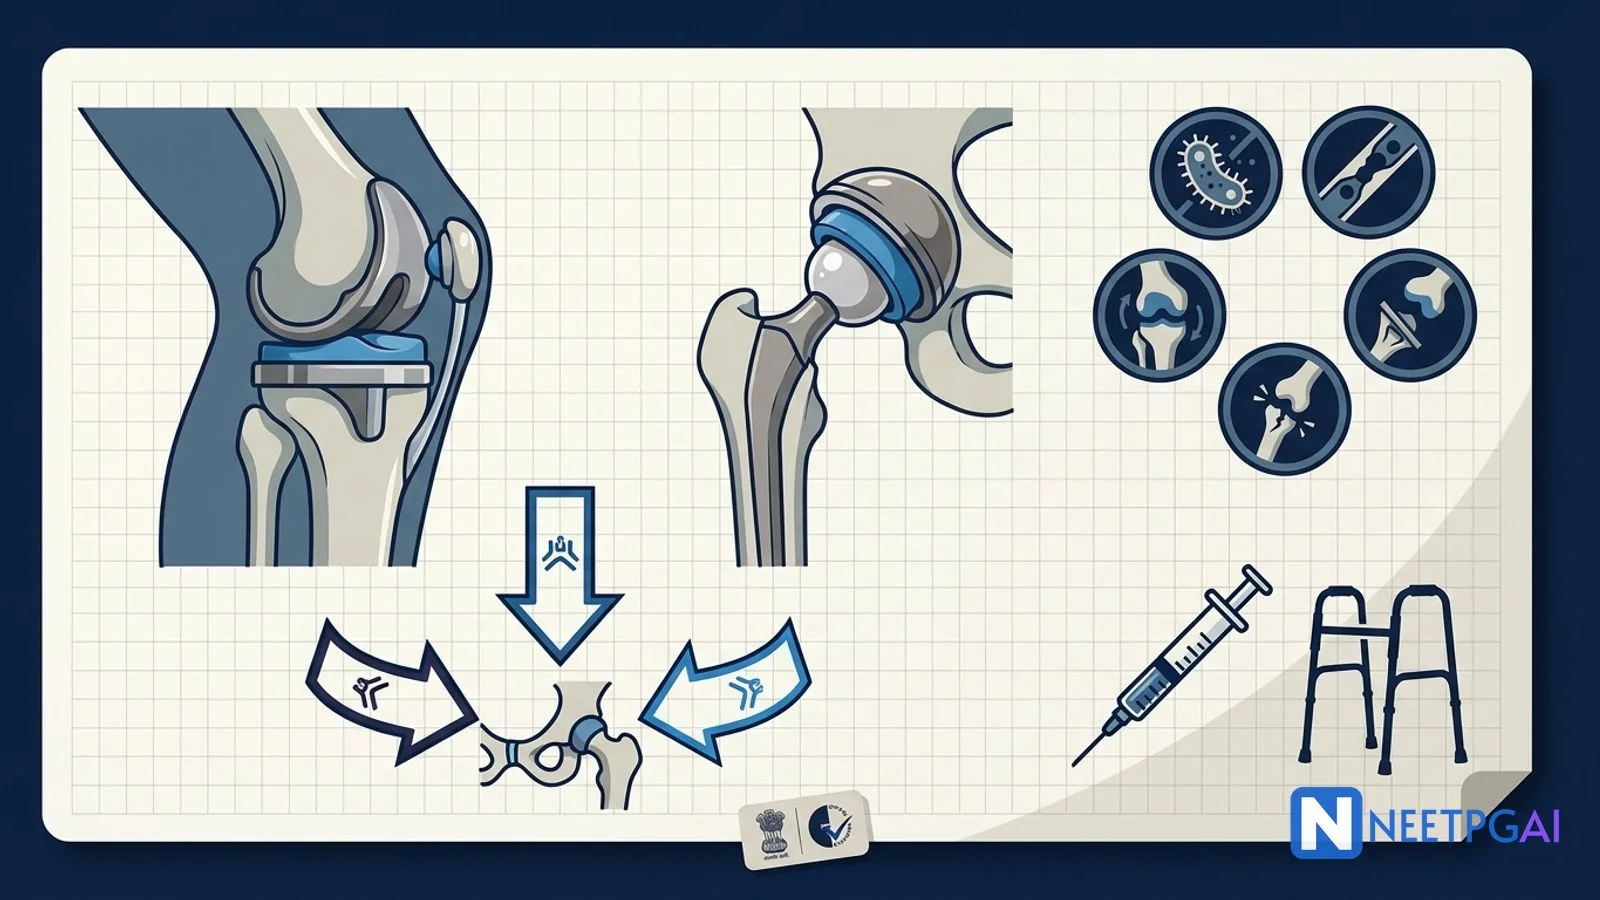
Joint replacement arthroplasty is a 1 to 2 question topic on NEET PG orthopaedics with heavy overlap into medicine (DVT prophylaxis) and public health (rehabilitation access). Lock these:
- TKA indication — end-stage tricompartmental OA with failed conservative treatment; commonest single indication is primary OA
- TKA contraindications — active infection (absolute), incompetent extensor mechanism (absolute); neuropathic joint, morbid obesity and high-demand young patient are relative
- THA approaches — posterior (highest dislocation), anterolateral, direct anterior (learning curve, higher fracture risk)
- Hip precautions after posterior approach — no flexion beyond 90 degrees, no crossing legs (adduction), no internal rotation for 6 weeks
- DVT prophylaxis — LMWH 28-35 days after THA, 10-14 days after TKA; add mechanical prophylaxis and early mobilisation
- Prosthetic joint infection — 1-2 percent primary; DAIR for early infection, two-stage revision for chronic
- Implant survival — 90 percent plus at 15 years for both TKA and THA in registry data
- India context — high OA burden from squatting toilets and traditional posture, PMJAY partial coverage, tertiary revision expertise concentrated in metros
Joint replacement arthroplasty transformed the natural history of end-stage arthritis in the last five decades. Sir John Charnley's low-friction hip in 1962 and Frank Gunston's condylar knee in 1968 laid the foundation for what is now one of the most predictably successful operations in surgery. For NEET PG, arthroplasty questions concentrate on indications, implant choices, surgical approaches, hip precautions, DVT prophylaxis, prosthetic joint infection classification, and long-term outcomes — with a growing Indian public-health dimension driven by rising obesity, traditional deep-squatting posture and PMJAY partial coverage of implants at empanelled hospitals.
This NEETPGAI deep dive walks through total knee arthroplasty (TKA) and total hip arthroplasty (THA) side by side. Pair this with the head and neck cancer guide and other orthopaedic topics for full surgical coverage.
Total knee arthroplasty (TKA)
Indications
- Primary osteoarthritis — the single commonest indication globally and in India
- Rheumatoid arthritis and other inflammatory arthritides (psoriatic, ankylosing spondylitis, juvenile idiopathic)
- Post-traumatic arthritis after tibial plateau or distal femoral fracture
- Avascular necrosis of the femoral condyles (steroid, sickle-cell, idiopathic)
- Haemophilic arthropathy — a specific paediatric-to-adult indication
- Failed conservative therapy — weight loss, physiotherapy, NSAIDs, intra-articular steroid or hyaluronic acid injections, unloader bracing, activity modification
- Significant functional disability — inability to walk more than a block, disturbed sleep from pain, dependence for basic activities of daily living, WOMAC or Oxford Knee Score in the severe range
Contraindications
Absolute:
- Active local or systemic infection
- Incompetent extensor mechanism that cannot be reconstructed
- Recurrent, uncontrolled sepsis at another site
Relative:
- Neuropathic (Charcot) joint — high failure rate
- Severe peripheral vascular disease
- Morbid obesity (BMI over 40) — higher infection, DVT, wound complications
- Young high-demand patient (heavy manual labour, athletics) — earlier revision
- Poorly controlled diabetes (HbA1c over 8 percent)
- Active smoking — wound and infection risk
- Non-adherence with rehabilitation
Pre-operative optimisation
Standing weight-bearing anteroposterior and lateral radiographs plus a skyline patellar view are the workhorse imaging modality; long-leg alignment films quantify varus or valgus deformity for template planning. MRI is not routinely needed for OA. Baseline CBC, coagulation profile, electrolytes, urinalysis, HbA1c, ECG and cardiology clearance if indicated are standard. Weight loss (target BMI under 35), smoking cessation for at least 4 weeks pre-operatively, dental review to eliminate oral sepsis, and screening for MRSA nasal carriage with decolonisation reduce infection rates.
Implant types
- Fixation: cemented (polymethylmethacrylate — the commonest in India, evidence-preferred in older patients), uncemented (press-fit with porous or hydroxyapatite coating for biological ingrowth) and hybrid (cemented tibia, uncemented femur)
- Bearing constraint: cruciate-retaining (CR) preserves the posterior cruciate ligament and offers a more natural kinematic profile; posterior-stabilised (PS) substitutes the PCL with a tibial post and femoral cam — chosen when the PCL is deficient or in inflammatory arthritis
- Mobile-bearing designs allow rotation between the polyethylene insert and the tibial tray — theoretically reduces contact stress; no clear long-term survivorship advantage over fixed-bearing
- Unicompartmental knee arthroplasty (UKA) — reserved for isolated medial or lateral compartment disease with an intact ACL, intact contralateral compartment and a correctable deformity; faster recovery, better range of motion, but higher revision rate
Complications
- Prosthetic joint infection — 1-2 percent primary, 3-5 percent revision; Staphylococcus aureus and coagulase-negative staphylococci dominate
- Venous thromboembolism — symptomatic DVT/PE 1-3 percent despite prophylaxis; higher without it
- Periprosthetic fracture — supracondylar femoral fracture is the commonest around a TKA; managed with locked plating or revision
- Aseptic loosening — historically driven by polyethylene wear and osteolysis; highly cross-linked polyethylene has reduced this
- Patellar clunk syndrome — fibrous nodule at the superior pole of the patellar prosthesis catches in the femoral intercondylar notch during knee extension (posterior-stabilised designs)
- Arthrofibrosis and stiffness — manipulation under anaesthesia at 6-12 weeks if flexion is under 90 degrees
- Persistent pain — up to 20 percent of patients remain dissatisfied despite a technically successful procedure; central sensitisation, unrealistic expectations and misaligned components contribute
Total hip arthroplasty (THA)
Indications
- Osteoarthritis — primary and secondary (developmental dysplasia, protrusio, slipped upper femoral epiphysis sequelae)
- Avascular necrosis of the femoral head — steroid, alcohol, sickle-cell, post-traumatic, idiopathic
- Rheumatoid arthritis and other inflammatory arthritides
- Post-traumatic arthritis after acetabular or femoral head/neck fracture
- Developmental dysplasia of the hip with secondary OA
- Neck of femur fracture — displaced intracapsular fracture in an active elderly patient (total hip preferred over hemiarthroplasty for higher functional demand)
For the truly frail, low-demand elderly patient with a displaced intracapsular neck of femur fracture, hemiarthroplasty (bipolar or unipolar) is preferred — shorter operation, lower dislocation rate, adequate functional outcome for a wheelchair or house-ambulant patient.
Bearing surfaces
- Metal-on-polyethylene (most common, cost-effective)
- Ceramic-on-polyethylene
- Ceramic-on-ceramic — low wear, but risk of squeaking, ceramic fracture
- Metal-on-metal — largely abandoned due to adverse local tissue reactions (ARMD), pseudotumour formation and systemic cobalt/chromium ion elevation; MHRA and FDA advisories restrict use
Surgical approaches
| Approach | Anatomy | Dislocation risk | Notes |
|---|
| Posterior (Moore, Southern) | Splits gluteus maximus, detaches short external rotators and posterior capsule | Highest historically (3-5 percent) — under 1 percent with capsular repair, larger heads, dual-mobility | Best acetabular exposure |
| Anterolateral (Hardinge) | Splits abductors (gluteus medius) between anterior and middle thirds | Lower | Abductor limp risk |
| Direct anterior (Smith-Petersen) | True internervous plane (superior gluteal / femoral) — muscle-sparing | Lower | Longer learning curve, higher intra-op fracture risk, lateral femoral cutaneous nerve neuropraxia |
Hip precautions after posterior approach
For 6 weeks after a posterior-approach THA (and often longer per surgeon preference):
- No hip flexion beyond 90 degrees — avoid low chairs, deep sofas, squatting
- No crossing legs (avoid adduction across midline) — sleep with abduction pillow
- No internal rotation — pivot away from the operated side
The dislocation position for a posterior-approach hip is flexion, adduction and internal rotation. For an anterior-approach hip the dislocation position is extension, adduction and external rotation — different precautions apply.
Complications
- Dislocation — highest with posterior approach; component malposition (cup anteversion outside the Lewinnek safe zone of 15 plus or minus 10 degrees anteversion and 40 plus or minus 10 degrees inclination) is a major risk
- Prosthetic joint infection — 1-2 percent primary
- Venous thromboembolism — highest risk of the major orthopaedic operations
- Leg length discrepancy — a common source of dissatisfaction and litigation
- Heterotopic ossification — periarticular bone formation, more with anterior and lateral approaches; NSAIDs (indomethacin) or low-dose radiotherapy for prophylaxis in high-risk patients
- Periprosthetic fracture (Vancouver classification A, B1, B2, B3, C) — around the femoral stem, especially with cementless press-fit
- Aseptic loosening and osteolysis — historically from polyethylene wear particles
- Squeaking (ceramic bearings)
- Metal-on-metal adverse reactions (ARMD) — pseudotumour, aseptic lymphocytic vasculitis-associated lesion (ALVAL)
- Sciatic nerve injury (posterior approach) and femoral nerve injury (anterior approach) — neuropraxia usually
Post-operative rehabilitation and DVT prophylaxis
- Early mobilisation on day 1 (or day of surgery in enhanced-recovery protocols)
- Weight bearing — as tolerated for cemented and most cementless implants; per surgeon for complex reconstructions
- DVT prophylaxis — LMWH (enoxaparin 40 mg subcutaneous once daily) for 28-35 days after THA and 10-14 days (up to 35 in high-risk) after TKA; alternatives include fondaparinux, apixaban, rivaroxaban, dabigatran, or aspirin in low-risk patients; mechanical prophylaxis with intermittent pneumatic compression and graduated compression stockings is added
- Physical therapy — quadriceps strengthening, range-of-motion, gait training with walker progressing to cane, functional milestones
- Return to sport — approximately 3 months for low-impact activity (cycling, swimming, golf, doubles tennis); high-impact activity (running, jumping, contact sports) is discouraged for both TKA and THA because of accelerated polyethylene wear and periprosthetic fracture risk
Prosthetic joint infection (PJI) — a NEET PG favourite
Tsukayama classification
| Type | Timing | Presentation | Management |
|---|
| Early post-operative | Within 4 weeks of surgery | Acute wound issues, systemic sepsis | DAIR (debridement, antibiotics, implant retention with modular exchange) |
| Late chronic | More than 4 weeks, indolent | Chronic pain, sinus, loosening on radiograph | Two-stage revision |
| Acute haematogenous | Well-functioning joint seeded by bacteraemia | Sudden pain, sepsis, distant source | DAIR if early; two-stage if delayed |
| Positive intra-operative cultures | Unexpected positive cultures at revision surgery | Silent | Extended antibiotics |
Diagnosis (MSIS criteria)
- Sinus tract communicating with the joint OR two positive cultures with the same organism OR three of the following: raised ESR/CRP, raised synovial WBC (over 3000 per microlitre with over 65-80 percent neutrophils), positive alpha-defensin, purulence around the prosthesis, single positive culture, positive histology (5 or more neutrophils per high-power field in 5 fields)
Common organisms
Staphylococcus aureus, coagulase-negative staphylococci (S. epidermidis biofilm), streptococci, gram-negatives (E. coli, Pseudomonas), anaerobes (Cutibacterium in shoulders), MRSA, Mycobacterium tuberculosis in India.
India-specific considerations
- High OA prevalence — cumulative epidemiological surveys estimate knee OA in 20-30 percent of adults over 45; obesity and traditional deep-squatting toilet posture are cited contributors, though the causal link between squatting and OA is contested in the literature
- Implant availability — indigenous manufacturers and generic implants have significantly reduced cost; premium imported implants remain available at private tertiary centres
- PMJAY (Ayushman Bharat) provides partial coverage for arthroplasty at empanelled hospitals, though co-payments and implant caps are common realities for patients
- Revision expertise is concentrated in metropolitan tertiary centres; peripheral hospitals often refer complex revision, PJI and periprosthetic fracture cases
- Rehabilitation access — outpatient physiotherapy is a genuine bottleneck; home-based programmes, community physiotherapists and telerehabilitation are increasingly used
- Age at presentation — Indian patients often present with more advanced disease and at younger ages than Western cohorts, raising the lifetime revision burden
- Squatting after arthroplasty — an important patient-education point given cultural practices around toilets, prayer and floor sitting; high-flexion knee designs and modified hip precautions are counselled
NEET PG MCQ traps
- Commonest indication for TKA — primary osteoarthritis
- Absolute contraindication to arthroplasty — active infection and incompetent extensor mechanism (for TKA)
- Highest dislocation risk THA approach — posterior (without capsular repair)
- Hip precautions after posterior approach — no flexion beyond 90 degrees, no adduction across midline, no internal rotation, for 6 weeks
- Anterior-approach dislocation position — extension, adduction, external rotation
- DVT prophylaxis duration — 28-35 days after THA, 10-14 days after TKA
- Commonest fracture around a TKA — supracondylar femoral fracture
- Vancouver classification — periprosthetic femoral fracture around a THA
- Tsukayama early PJI — within 4 weeks; DAIR
- Chronic PJI management — two-stage revision with antibiotic-loaded cement spacer, 6-8 weeks IV antibiotics, reimplantation
- Girdlestone procedure — resection arthroplasty of the hip for uncontrollable infection
- Metal-on-metal complication — ARMD (adverse reaction to metal debris), pseudotumour, cobalt/chromium ion elevation
- Bearing choice associated with squeaking — ceramic-on-ceramic
- Lewinnek safe zone — cup anteversion 15 plus or minus 10 degrees and inclination 40 plus or minus 10 degrees
- Patellar clunk — posterior-stabilised TKA design
- UKA prerequisites — isolated compartmental disease, intact ACL, correctable deformity
- Hemiarthroplasty vs THA in NOF fracture — hemi for frail low-demand elderly; THA for active elderly
- Prophylactic antibiotic for arthroplasty — cefazolin (or vancomycin/teicoplanin for MRSA-positive) within 60 minutes of incision
- Highly cross-linked polyethylene — reduces wear and osteolysis compared to conventional UHMWPE
- Revision survival is lower than primary — a recurring exam concept
Frequently asked questions
What are the accepted indications and contraindications for total knee arthroplasty?
Total knee arthroplasty is offered for end-stage tricompartmental disease with disabling pain, stiffness, and functional loss unresponsive to a documented course of conservative therapy (weight loss, physical therapy, activity modification, analgesics, intra-articular injections). The commonest single indication is primary osteoarthritis; other indications include rheumatoid arthritis, post-traumatic arthritis, avascular necrosis of the femoral condyles, seronegative spondyloarthropathies and haemophilic arthropathy. Absolute contraindications are active local or systemic infection and an incompetent extensor mechanism that cannot be reconstructed. Relative contraindications are neuropathic (Charcot) joint, severe peripheral vascular disease, poorly controlled diabetes or morbid obesity (BMI over 40), a young patient with high-demand occupational or sporting requirements, and a non-adherent patient in whom post-operative rehabilitation is unlikely.
Which surgical approach for total hip arthroplasty has the highest dislocation risk and why?
The posterior (Moore, Southern) approach has historically been associated with the highest dislocation rate — up to 3-5 percent without capsular repair. It splits gluteus maximus, detaches the short external rotators (piriformis, obturator internus, gemelli, quadratus femoris) and the posterior capsule, giving excellent acetabular exposure but leaving the joint most vulnerable posteriorly in the position of flexion, adduction and internal rotation. Modern practice reduces this rate to under 1 percent with meticulous posterior capsular and short-rotator repair, larger femoral heads (36 mm or above), dual-mobility bearings and appropriate cup anteversion. Anterolateral (Hardinge) and direct anterior approaches have lower reported dislocation but the direct anterior route has a longer learning curve, higher intra-operative femoral fracture risk and lateral femoral cutaneous nerve neuropraxia.
What is the standard DVT prophylaxis regimen after major lower limb arthroplasty?
Symptomatic venous thromboembolism affects 1-3 percent of arthroplasty patients despite prophylaxis; asymptomatic DVT rates on venography are substantially higher. Current guidelines (AAOS, NICE, ICM) recommend extended chemoprophylaxis for 28-35 days after total hip arthroplasty and 10-14 days (up to 35 days in high-risk patients) after total knee arthroplasty. Options include low molecular weight heparin (enoxaparin 40 mg subcutaneous once daily), fondaparinux, apixaban, rivaroxaban, dabigatran, or in low-risk patients aspirin 81-325 mg twice daily. Mechanical prophylaxis (intermittent pneumatic compression, graduated compression stockings) and early mobilisation are added universally. In the Indian context aspirin plus mechanical prophylaxis is common because of cost, bleeding concerns and lower absolute VTE incidence in South Asians.
How is prosthetic joint infection classified and initially managed?
Prosthetic joint infection complicates 1-2 percent of primary and 3-5 percent of revision arthroplasty. The Tsukayama classification is time-based — early post-operative (within 4 weeks of surgery), late chronic (more than 4 weeks after surgery, indolent course), acute haematogenous (well-functioning joint seeded by bacteraemia) and positive intra-operative cultures at revision. Diagnosis relies on synovial fluid analysis (WBC over 3000 per microlitre with over 65-80 percent neutrophils in a chronic infection), raised ESR and CRP, alpha-defensin and multiple intra-operative tissue cultures. Early post-operative and acute haematogenous infections in a well-fixed prosthesis may be managed by debridement, antibiotics and implant retention (DAIR) with modular component exchange. Chronic infection requires a two-stage revision — implant removal, antibiotic-loaded cement spacer, 6-8 weeks of pathogen-directed IV antibiotics, then reimplantation. Single-stage revision, resection arthroplasty (Girdlestone for hip) and rarely arthrodesis or amputation are reserved for specific scenarios.
What long-term implant survival can patients expect from primary hip and knee replacement?
Contemporary primary total knee arthroplasty achieves a 90-95 percent 15-year implant survivorship in registry data (Australian AOANJRR, National Joint Registry England and Wales, Swedish Knee Register). Total hip arthroplasty with modern cementless titanium stems, highly cross-linked polyethylene and ceramic bearings achieves 90-95 percent survivorship at 15 years and 80-85 percent at 25 years — the ODEP 10A star rating is a useful benchmark. Failure modes have shifted over three decades from polyethylene wear and osteolysis (older conventional polyethylene) to aseptic loosening, instability, infection and periprosthetic fracture. Revision surgery is technically more complex, has a higher complication rate and shorter survival than primary arthroplasty, which is why implant longevity matters most in younger patients — the Indian aspirant should remember that a patient in their fifties may outlive one, and possibly two, primary implants.
This content is for educational purposes for NEET PG exam preparation. It is not a substitute for professional medical advice, diagnosis, or treatment. Clinical information has been reviewed by qualified medical professionals.
Written by: NEETPGAI Editorial Team
Reviewed by: Pending SME Review
Last reviewed: September 2026